You suspect revenue is leaking. Denial patterns don't match what you've read about ambulatory practices. Your A/R aging looks off compared to generic benchmarks, and you can't tell whether the problem is your workflows or just the reality of running a PT clinic with heavy Medicare volume.
Medical billing metrics have formulas and thresholds. But PT-specific payer mix and high-frequency visit patterns change what "good" actually means. Rehab therapy benchmarks differ from generic medical ones in ways that directly affect your revenue.
Below, you'll see exactly where your numbers fall against PT-specific standards. You'll also learn which gaps are costing your clinic money.
Medical billing metrics go by several names—KPI metrics for medical billing or revenue cycle management key performance indicators. Whatever you call them, they reveal whether your practice is converting care into cash.
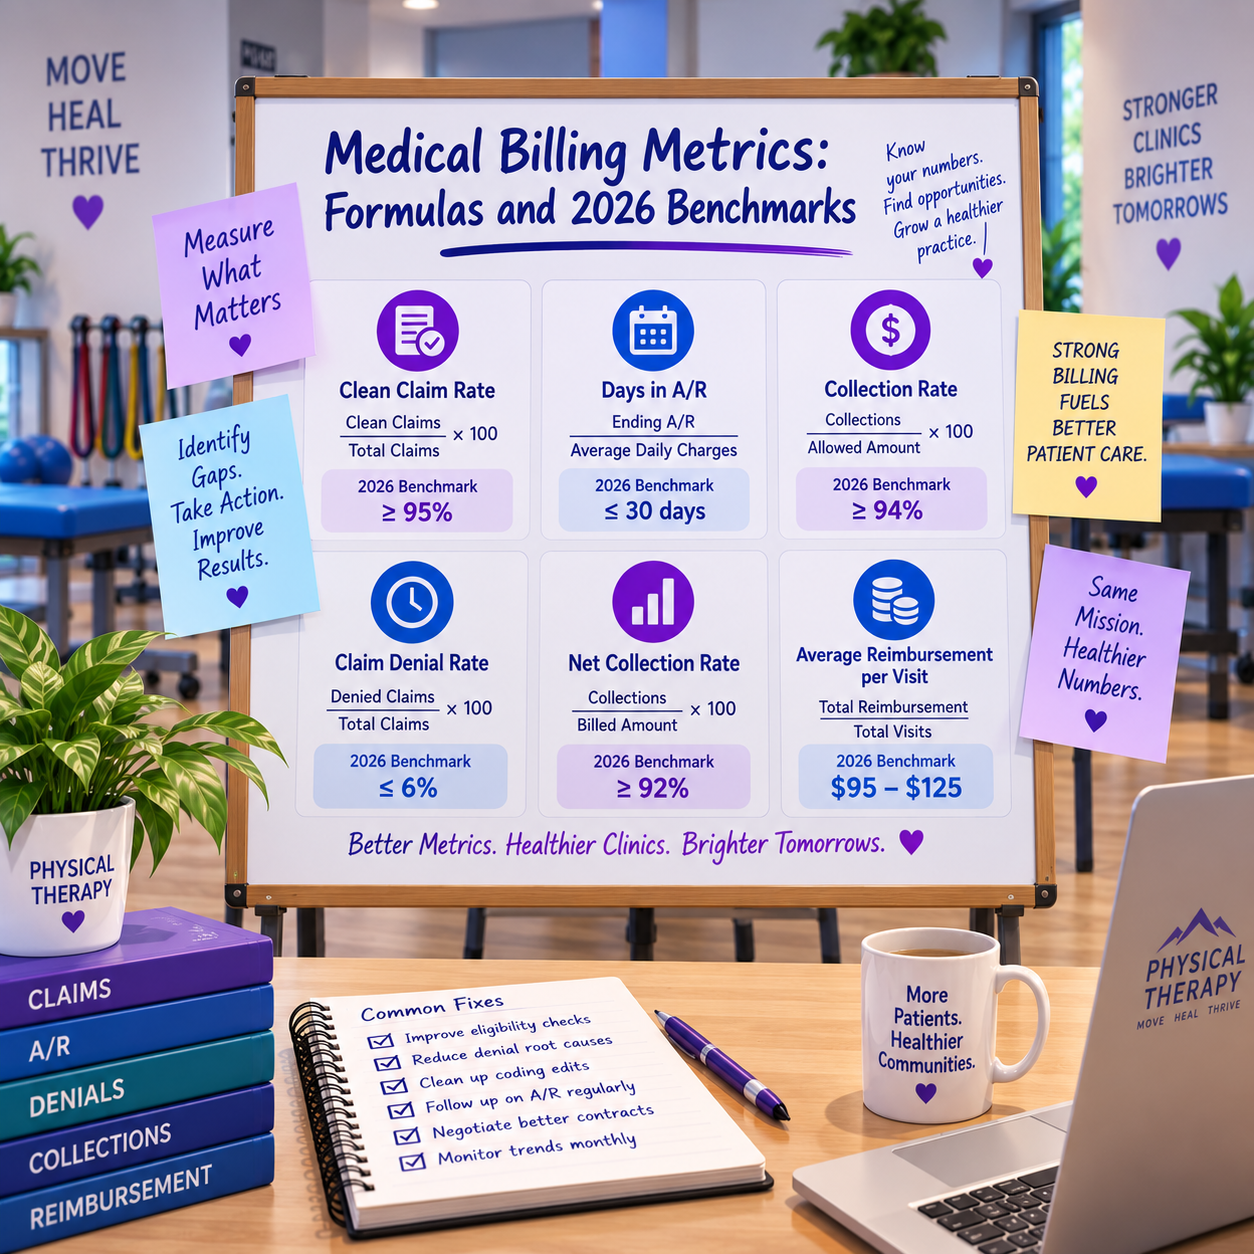
The problem is that standard healthcare benchmarks weren't built for rehab therapy. Heavy Medicare and MA volume, workers' comp cases, and high-frequency visit patterns all shift what "good" looks like. The table below puts all eleven formulas and dual-tier benchmarks in one place.
Top-tier benchmarks sourced from HFMA MAP Award Statistical Data, 2024.
Six metrics determine how fast money reaches your bank account and how much of what you earned you actually keep.
Formula: Total A/R ÷ Average Daily Charges = Days in A/R
Industry benchmark: < 35 days.
Top-tier: < 30 days; HFMA MAP Award winners averaged roughly 22 days.
If your practice carries significant Medicare or Medicare Advantage volume, expect this number to run a few days longer than commercial-heavy clinics. More than half of eligible Medicare beneficiaries—54%—are now enrolled in MA plans according to KFF. Those plans layer on prior authorization requirements and slower processing timelines.
Financial impact: If your practice runs $50K in average daily charges, reducing Days in A/R from 35 to 25 days releases $500K in working capital.
If This Metric Is Off: Start with charge lag. If claims aren't leaving within 48 hours, the A/R clock is already running late. Then pull your A/R aging report to pinpoint where dollars are stuck.
Your A/R aging report works as a pyramid. A healthy distribution concentrates dollars at the base: 50–60% of total A/R in the 0–30 day bucket, less than 10% in 61–90 days, and under 8% past 90 days for insurance A/R. Patient A/R ages differently due to payment plans and collections timelines.
Insurance A/R >90 days benchmark: < 8%
Patient A/R >90 days benchmark: < 20%
According to the KFF Employer Health Benefits Survey, 27% of covered workers now carry high-deductible health plans. More of what you're owed sits with patients, not payers. Tracking these separately shows whether your problem is payer delays or patient collections.
If This Metric Is Off: A growing 61–90 insurance aging bucket usually means denials are not being followed up on quickly enough. Rising patient balances over 90 days often indicate unworked accounts and inconsistent collection follow-up.
Net collection rate formula: Payments Collected ÷ (Charges − Contractual Adjustments) × 100 = NCR
Benchmark: > 95%. Top-tier: > 98%
For PT clinics with heavy Medicare contracts, NCR is the collection metric that matters most. It strips out the contractual write-downs you've already agreed to. Then it measures how much of what you were actually allowed to collect you captured.
Financial impact: A practice collecting $10.2M annually on $11.5M allowed (after contractual adjustments) = 88.69% NCR. If NCR improved to 96%, that's an additional $84K/month or $1.01M annually.
Average Revenue Per Visit (ARPV) formula: Total Collections ÷ Total Visits = ARPV
ARPV is simpler than NCR and more intuitive for spotting reimbursement erosion. If your ARPV was $125 six months ago and has fallen to $115 today, you need to act now. Track this month-to-month. There's no universal benchmark because PT specialties vary, but the trend line tells the story.
If NCR or ARPV Is Off: Compare ERA (Electronic Remittance Advice) postings against your contracted fee schedules. Payer underpayments that go uncontested chip away at both metrics without ever triggering a denial. Review your write-off workflow. Balances written off before staff confirm whether they're appealable or collectible from the patient drop NCR even when claims are clean.
Formula: Bad Debt Write-Offs ÷ (Charges − Contractual Adjustments) × 100
Benchmark: < 3%. Top-tier: < 2%
This metric separates expected contractual adjustments from revenue you should have collected but didn't—whether from payers or patients.
If This Metric Is Off: Audit what you're writing off. If small balances are written off without checking whether they're patient responsibility or appealable, bad debt climbs even when your claims are clean.
Formula: Total Billing Costs ÷ Total Revenue Collected × 100
Benchmark: < 5%. Top-tier: < 4%
This metric answers a simple question: is your billing operation worth the cost relative to what it brings in? Include staff salaries, clearinghouse fees, software subscriptions, and outsourced billing fees.
If This Metric Is Off: Look for rework caused by disconnected systems. When notes live in one tool and billing in another, manual charge entry inflates this number fast.
Four metrics measure whether claims leave your office accurate and on time.
Initial denial rate formula: Denied Claims (First Submission) ÷ Total Claims Submitted × 100
Benchmark: 6–10%. Top-tier: < 5%; HFMA MAP Award winners posted roughly 2.4%
Final denial rate formula: Claims Still Denied After Appeals ÷ Total Claims Submitted × 100
Benchmark: 2–5%. Top-tier: < 2%
The gap between these two metrics shows whether your denial management and appeals process is working. You could have 8% initial denials but only 2% final denials. That's a strong appeals process recovering revenue.
Denial pressure is climbing. Sixty percent of medical group leaders reported higher denial rates in 2024 compared to the prior year, according to an MGMA Stat poll. For PT clinics, the triggers are specific: prior auth failures (especially on MA plans), medical necessity challenges, and timed-unit coding errors.
CMS's 2024 CERT (Comprehensive Error Rate Testing) data narrows it further. For therapy services, the top improper payment causes are a missing plan of care, missing certification or recertification, and missing progress reports.
A regulatory shift on the horizon could ease some of this friction. Starting January 1, 2026, most impacted payers must return PA decisions within 72 hours for urgent requests and 7 calendar days for standard ones, per a CMS final rule.
If This Metric Is Off: Pull your top three denial reason codes. In most PT practices, prior auth and medical necessity account for the bulk. Real-time eligibility checks and built-in code scrubbing catch most of these before a claim ever goes out. Confirm that every claim includes required therapy documentation—plan of care, cert/recert, progress report—before submission.
Formula: Claims Accepted on First Submission ÷ Total Claims Submitted × 100
Benchmark: 90–95%
A claim can sail through the clearinghouse—technically "clean"—and still require manual follow-up before a payer releases payment. In a high-volume PT practice, every claim that needs a phone call or resubmission adds up fast. Part of the drag is structural: only 35% of prior authorizations are fully electronic today, per Forbes.
If This Metric Is Off: Determine where claims are failing. At the clearinghouse level, the problem is coding or formatting errors. At the payer level, it's missing auth or medical necessity. The fix is different for each. Make sure documentation is complete before charges go out. Incomplete plans of care and missing progress notes are the most common payer-level rejection triggers in therapy.
Formula: Average Days from Date of Service to Claim Submission = Charge Lag
Benchmark: < 48 hours. HFMA MAP winners averaged about 2.2 days.
In PT clinics, high charge lag almost always has the same story: therapists charting after hours. When notes aren't wrapped up the same day, charges can't move to billing. Every day of delay adds directly to your Days in A/R.
Financial impact: At $50K average daily charges, reducing charge lag from 5 days to 2 days accelerates $150K in cash flow.
If This Metric Is Off: Monitor note completion rates by therapist. If notes aren't finalized the same day, that's your charge lag source. PT-specific templates and smart pre-population can shave enough documentation time to keep charting in the clinic.
You now have the formulas, benchmarks, and tools to identify where revenue cycle problems are occurring—whether that’s charge lag, denial trends, or collection rates that shift once payer mix is taken into account.
Empower EMR bridges the gap between knowing your numbers and actually improving them. Documentation flows directly into billing. Therapists finish notes before they leave for the day. Claims go out with the right codes and required documentation attached. The metrics that matter most improve without extra steps or added staff.
See how Empower EMR turns billing metrics into better cash flow. Schedule a demo.
Review Days in A/R, initial denial rate, and clean claim rate weekly to catch problems early. Run a full dashboard monthly to track trends.
Weekly checks focus on leading indicators like charge lag and denial spikes. Monthly reviews measure collection rates and A/R aging distribution against benchmarks. Set alerts for sudden changes. A denial rate jump over 2% week-over-week often signals a workflow break or payer policy shift.
Expect 60–90 days if the root cause is charge lag or submission delays. Fixing charge lag delivers the fastest improvement because it stops new A/R from starting late.
Clearing aged A/R in the 61–90 and 90+ buckets takes longer. Denials need appeals or write-offs. Patient balances require payment plans or collections follow-up.
You're losing revenue to underpayments. Payers are paying less than contracted rates. Early write-offs cause losses too, when balances are written off without verifying appeal or patient-pay options.
Compare ERA postings against your contracted fee schedules to catch underpayments that bypass denials but still cut into NCR. Audit your write-off process. If staff write off small balances without checking whether they're patient responsibility or appealable, NCR drops even when claims are clean.
Yes. Payer-specific benchmarks reveal whether problems are systemic or isolated to one payer type.
Medicare and MA typically extend Days in A/R by 3–5 days versus commercial due to prior authorization and slower processing. Workers' comp adds case management layers that inflate both Days in A/R and denial rate. If one payer class is an outlier, the fix is different. Commercial denials often stem from eligibility gaps, while MA denials cluster around prior auth and medical necessity.
Initial denial rate shows how clean your claims are on first submission. Final denial rate shows how effective your appeals process is at recovering revenue.
A practice with 8% initial denials but 2% final denials has a strong appeals workflow recovering 75% of initially denied claims. That's worth preserving. A practice with 8% initial and 7% final denials has a broken appeals process. Most denials become write-offs.